
Why Do Babies Fart So Much: Causes And Helpful Tips

Introduction
For parents in the United States, frequent baby gas is one of the most common early concerns. Most babies fart often because their digestive systems are still developing, and they may swallow air while crying, feeding, or using a bottle. In many cases, gas is normal and improves as feeding skills and gut movement mature.
Gas may still make a baby fussy. The goal is not to stop every fart. The goal is to ease discomfort, support safe feeding, and spot signs that need medical care.
Why do babies fart so much?
Babies fart often because they swallow air and have immature digestion. Their small stomachs fill quickly, their feeding patterns change often, and they may not yet have good control of the muscles used to release gas.
Common causes include:
- Swallowing air during breast or bottle feeding
- Crying for long periods
- Feeding too fast
- A poor bottle latch
- An uneven breastfeeding latch
- Normal movement of milk through the intestines
- Constipation or hard stools
- Sensitivity to a formula ingredient
- A food protein allergy, which is less common
A baby may also grunt, turn red, pull up their legs, or strain before passing gas. These signs can look painful, but they do not always mean something is wrong.
Immature digestion
A young baby’s digestive system is still learning how to coordinate eating, moving stool, and passing gas. The muscles of the belly and pelvic floor may not work together smoothly yet.
This can cause a baby to strain, cry, or make loud sounds before passing soft stool or gas. This pattern is often called infant dyschezia. It usually improves on its own as the baby matures.
Swallowed air
Babies can swallow air when they:
- Feed while very hungry
- Cry before or during a feed
- Have trouble staying latched
- Use a bottle with a fast-flow nipple
- Drink from a bottle while lying flat
- Pause often during a feed
Some swallowed air comes back up as a burp. The rest moves through the intestines and leaves as a fart.
Normal gut bacteria
Bacteria in the intestines help break down milk and other food. This process can create gas. A baby’s gut bacteria change during the first months of life, so gas may come and go without a clear reason.
There is no single “normal” number of farts per day. Frequency matters less than the baby’s overall health, feeding, growth, stool pattern, and behavior.

Is it normal for a newborn to fart a lot?
Yes. Frequent farting is usually normal when a newborn feeds well, has regular wet diapers, and seems well between episodes of fussiness.
A newborn may pass gas many times during the day. Some babies seem to have more gas in the evening. Others pass gas during or soon after feeding.
A healthy newborn may also:
- Burp often
- Make grunting sounds
- Bring up small amounts of milk
- Draw up their legs
- Strain before passing soft stool
- Have short periods of crying
These signs can be normal if the baby is growing and does not appear seriously ill.
Gas versus a more serious problem
Gas usually causes short periods of discomfort that improve after a burp, fart, stool, position change, or feed.
A medical problem may cause symptoms that are severe, persistent, or linked with poor feeding, vomiting, fever, blood in the stool, or poor weight gain.
The pattern matters. A baby who passes gas but settles, feeds well, and has normal wet diapers is less concerning than a baby who has a swollen belly and refuses several feeds.
How can you tell if gas is hurting your baby?
Gas may be causing discomfort when a baby:
- Cries during or after feeds
- Pulls their knees toward the belly
- Clenches their fists
- Arches their back
- Turns red while straining
- Has a tight-looking belly that later softens
- Calms after burping or passing gas
These signs are not specific to gas. Hunger, tiredness, reflux, a wet diaper, overheating, and illness can look similar.
A simple pattern can help. Note when the crying starts, how long it lasts, whether it follows a feed, and what helps. Share this record with the baby’s pediatrician if the problem continues.

How to help a gassy baby
Small feeding and movement changes may reduce swallowed air and help gas move through the intestines. Try one change at a time so you can tell what helps.
1. Check the feeding position
Keep the baby’s head higher than the stomach during feeding. The baby’s neck should stay straight, not bent sharply forward or backward.
For bottle feeding, hold the bottle at an angle that keeps the nipple full of milk. This may reduce the amount of air the baby takes in.
Never prop a bottle. Bottle propping can raise the risk of choking, ear infections, and overfeeding.
2. Pause to burp
Burp the baby during and after a feed. Some babies need a pause halfway through a bottle. Breastfed babies may need a burp when switching breasts.
Use a gentle method:
- Hold the baby upright against your chest or support the baby sitting on your lap.
- Support the head and neck.
- Pat or rub the back gently.
- Stop after a few minutes if no burp comes.
Not every baby burps each time. A missing burp does not prove that gas is trapped.
3. Check the bottle nipple flow
A nipple that flows too fast can make a baby gulp, cough, or pull away. A nipple that flows too slowly may frustrate the baby and lead to more sucking and air intake.
Use the nipple flow recommended for the baby’s age and feeding skill. Do not enlarge a nipple hole at home. If the baby coughs, chokes, leaks milk from the mouth, or takes a very long time to feed, ask the pediatrician or feeding specialist to assess the feed.
4. Keep the baby upright after feeding
Hold the baby upright for about 20 to 30 minutes after a feed if spit-up or gas is a concern. Keep the baby awake and supervised during this time.
When the baby sleeps, place the baby flat on their back on a firm, empty sleep surface. Do not use inclined sleepers, sleep positioners, wedges, or pillows to treat gas or reflux.
5. Try gentle leg movement
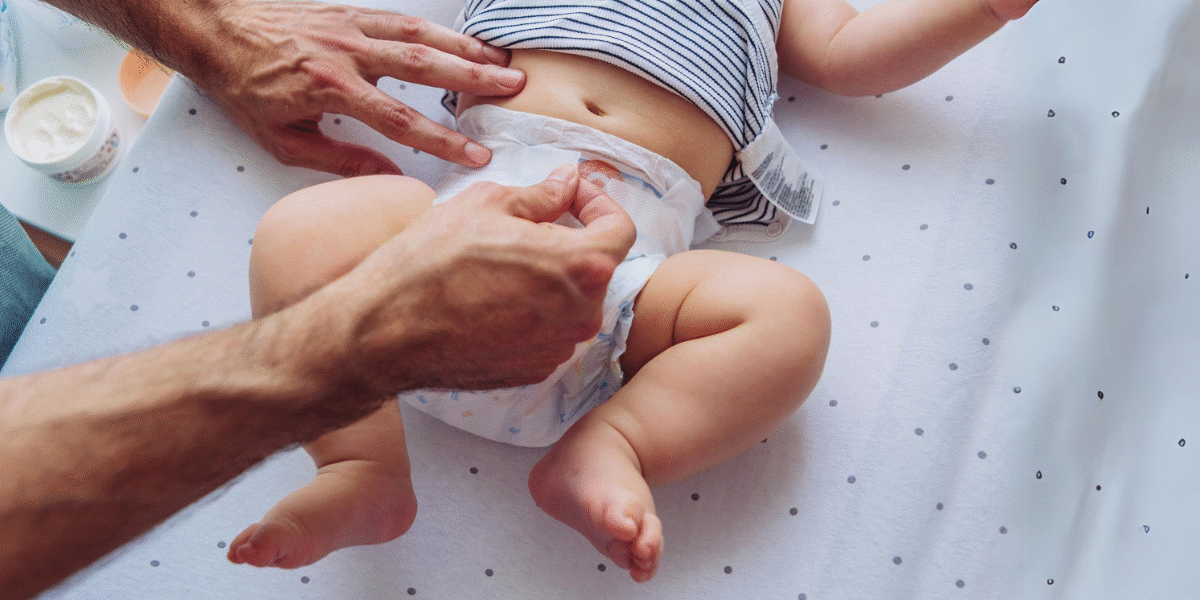
When the baby is awake and calm, lay the baby on their back. Move the legs slowly in a bicycle motion. You can also bring both knees gently toward the belly and then release them.
Stop if the baby resists, cries harder, or seems in pain. Never press hard on the belly.
6. Give supervised tummy time
Tummy time can help babies build strength and may help move gas. Only do it when the baby is awake and watched closely.
Place the baby on a firm floor mat or across your chest. Start with short sessions and add time as the baby tolerates it. Always return the baby to their back for sleep.
7. Review the latch
During breastfeeding, a deep latch can reduce air intake. Signs of a good latch may include:
- The baby’s mouth is wide open
- More areola shows above the upper lip than below the lower lip
- The lips turn outward
- Sucking is not sharply painful
- The baby makes few clicking sounds
- Milk transfer seems steady
A lactation consultant can check the latch. In the United States, parents can also ask the baby’s pediatrician about local breastfeeding support.
Can breastfeeding foods cause baby gas?
Usually, a breastfeeding parent does not need to avoid a long list of foods. Gas in a baby is not proof that a specific food caused it.
Some babies may react to a protein from the breastfeeding parent’s diet, most often cow’s milk protein. This is different from ordinary gas. Possible signs include blood or mucus in the stool, eczema, repeated vomiting, feeding trouble, wheezing, or poor weight gain.
Do not remove many foods without medical guidance. Broad food restrictions can make it harder for the breastfeeding parent to get enough calories and nutrients.
If the pediatrician suspects a food protein allergy, they may recommend a short, planned elimination trial followed by a careful reintroduction. The exact plan depends on the baby’s symptoms and health.
Does formula cause gas?
Formula can contribute to gas for some babies, but frequent gas does not automatically mean the formula is wrong.
Switching formulas often may upset feeding and make it harder to identify the cause. Do not dilute formula, add extra powder, or change the mixing method. Incorrect mixing can cause serious nutrition and fluid problems.
Ask the pediatrician before changing formula, especially if the baby has:
- Poor weight gain
- Repeated vomiting
- Blood in the stool
- Ongoing diarrhea
- A widespread rash
- Significant feeding distress
Some special formulas are made for specific medical needs. A “sensitive,” lactose-free, or extensively hydrolyzed formula is not right for every gassy baby.
What about lactose intolerance?
True lactose intolerance is uncommon in young full-term infants. Babies naturally digest lactose, the main sugar in breast milk and standard infant formula.
Temporary lactose intolerance can occur after some intestinal illnesses. Congenital lactose intolerance is rare and usually causes severe diarrhea and poor growth from early life. Talk with a pediatrician before using lactose-free formula.

Do gas drops, gripe water, or probiotics help?
Some over-the-counter products may not help, and “natural” does not always mean safe for babies.
Simethicone gas drops
Simethicone is sold as a gas-relief medicine. Research has not shown consistent benefit for infant colic or ordinary baby gas. Ask the pediatrician or pharmacist before giving it, and follow the product label exactly.
Do not give adult products to an infant.
Gripe water
Gripe water products vary. They are not required for normal infant gas, and some contain herbs, sweeteners, or other ingredients that may not be suitable for babies.
The American Academy of Pediatrics advises against giving infants water, juice, or other drinks unless a health professional recommends them. Breast milk or properly prepared infant formula provides the fluid babies need in early infancy.
Probiotics
Evidence for probiotics depends on the exact strain, dose, age, feeding method, and condition being treated. A product that helps one group of babies may not help another.
Do not start a probiotic for a premature baby, medically fragile baby, or young infant without medical advice. Ask the pediatrician which evidence applies to your baby.

When should you call the pediatrician about baby gas?
Call the pediatrician if gas is ongoing and your baby:
- Is not feeding well
- Has fewer wet diapers than usual
- Is not gaining weight
- Vomits often
- Has diarrhea that continues
- Has blood or black stool
- Has a rash with feeding symptoms
- Cries for long periods and cannot be comforted
- Has a belly that stays swollen or feels hard
- Seems unusually sleepy or weak
A newborn with a fever needs prompt medical advice. For babies younger than 3 months, a rectal temperature of 100.4°F (38°C) or higher requires immediate contact with a health professional, according to the American Academy of Pediatrics.
Seek emergency care now for these signs
Call 911 or seek emergency care if the baby:
- Has trouble breathing
- Has blue, gray, or very pale skin
- Is difficult to wake
- Has a seizure
- Has repeated green or bright yellow vomit
- Has severe belly swelling
- Has signs of dehydration and cannot feed
- Has sudden severe pain or inconsolable crying
Green vomit can signal an intestinal blockage. It is not something to treat as simple gas at home.

Common mistakes parents make when treating gas
Several well-meant steps can create new problems.
Changing formula too often
Frequent changes can make symptoms harder to track. Discuss a planned change with the pediatrician instead.
Using food or water too early
Do not give water, tea, juice, cereal, or solid food to treat gas unless the baby’s clinician tells you to do so. Young infants need breast milk or correctly prepared formula.
Putting a baby to sleep upright
Upright holding after a feed may help while the baby is awake. It is not a safe sleep position. Babies should sleep flat on their backs on a firm, clear surface.
Pressing on the belly
Deep massage or forceful knee-to-belly movements can hurt. Use slow, gentle touch only.
Blaming every cry on gas
Crying can come from hunger, tiredness, heat, cold, reflux, illness, or the need for comfort. Check the full picture instead of focusing on farting alone.
How long does baby gas last?
Gas often improves over the first few months as a baby learns to feed, burp, digest, and pass stool more easily. The timing varies.
Some babies improve around 3 to 4 months. Others have symptoms longer, especially when crying, reflux, constipation, or feeding problems are also present.
There is no exact age when gas must stop. The important signs are steady growth, good feeding, normal wet diapers, and periods when the baby is comfortable.
What should you track before a medical visit?
A short log can help the pediatrician find patterns. Record:
- Baby’s age
- Breast milk, formula, or both
- Amount and timing of feeds
- Bottle nipple type and flow
- Burping and spit-up
- Stool color and texture
- Wet diaper count
- Crying times and duration
- Fever or vomiting
- Any formula or diet changes
A video of unusual breathing, feeding, or stooling may also help. Do not delay urgent care while collecting notes.
FAQs about babies who fart a lot
Is it normal for a baby to fart but not poop?
Yes. A baby may pass gas without having a bowel movement. Breastfed babies can sometimes go several days between stools, while formula-fed babies often stool more regularly. The stool should be soft, and the baby should feed and act well.
Why does my baby fart at night?
Gas may seem worse at night because babies are tired, feed more often, or cry more during that time. A quiet evening routine, calm feeding, burping, and supervised upright holding while awake may help. Nighttime gas alone does not mean the baby has a disease.
Why does my baby fart while breastfeeding?
A baby may swallow air because of a fast milk flow, a shallow latch, crying during the feed, or frequent pulling on and off the breast. Clicking sounds, coughing, leaking milk, or painful nursing can point to a latch or flow issue. A lactation consultant can help assess it.
Can overfeeding cause gas?
It can. A baby who takes more milk than they can comfortably handle may spit up, gulp, or seem uncomfortable. Follow the baby’s hunger and fullness cues rather than urging the baby to finish a bottle. Ask the pediatrician about feeding amounts if you are unsure.
Does a farting baby need to be burped every time?
No. Some babies burp quickly, while others do not need to burp after every feed. Hold the baby upright and try gently for a few minutes. If the baby is comfortable, there is no need to keep trying.
Should I use a rectal thermometer to help my baby poop or pass gas?
Do not use rectal stimulation as a routine gas treatment unless a clinician specifically teaches you to do so. Repeated stimulation can irritate the rectum and may hide a feeding or stool problem. Ask the pediatrician about constipation instead.
Key takeaways
- Babies fart often because they swallow air and have developing digestive systems.
- Gas is usually normal when the baby feeds well, grows, and has normal wet diapers.
- Gentle burping, good feeding position, supervised tummy time, and slow leg movement may help.
- Avoid water, gripe water, unapproved medicines, formula dilution, and unsafe sleep positions.
- Call the pediatrician for poor feeding, poor weight gain, blood in the stool, repeated vomiting, or a hard swollen belly.
- Get urgent care for breathing trouble, blue skin, severe swelling, green vomit, extreme sleepiness, or a fever in a baby younger than 3 months.
Conclusion
Most babies fart a lot because their bodies are learning how to feed and digest milk. Frequent gas can be loud and upsetting, but it is often a normal stage rather than a sign of illness.
Use gentle feeding and movement steps, keep sleep practices safe, and watch the baby’s overall health. When gas comes with poor feeding, fever, repeated vomiting, blood in the stool, dehydration, or severe distress, contact a pediatrician promptly.
Evidence reviewed: American Academy of Pediatrics and HealthyChildren.org guidance on newborn fever, safe sleep, feeding, and infant symptoms; Centers for Disease Control and Prevention guidance on infant feeding; National Institute of Diabetes and Digestive and Kidney Diseases information on gastrointestinal symptoms. Guidance can change, so families should use current advice from the baby’s health professional.





